Ongoing Research Projects 2 projects
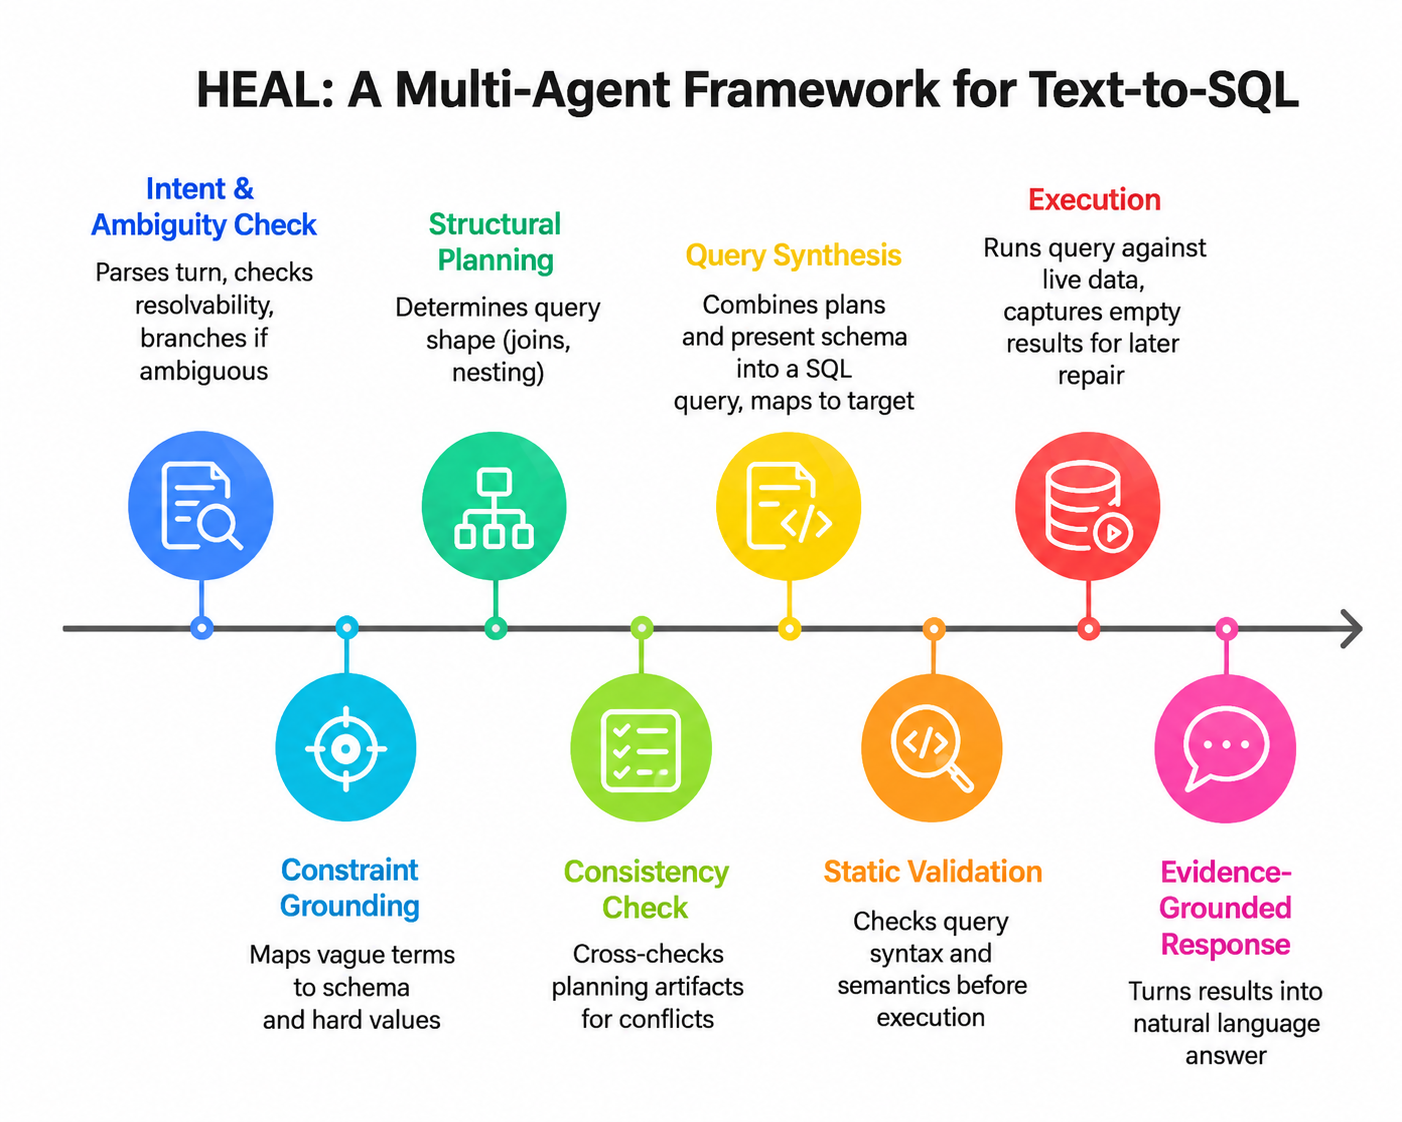
HEAL: A Multi-Agent Framework with Disagreement-Gated Validation for Reliable Text-to-SQL on Clinical Patient Records
July 2026 to Present
Clinicians need to ask natural-language questions over patient databases across multi-turn conversations, not just isolated questions. Answering correctly requires jointly handling four coupled challenges: ambiguity (mapping informal language like “high blood pressure” to schema literals, and resolving coreference like “those patients” across turns), nested reasoning (questions like “latest HbA1c per patient” that need subqueries or ranking, not a flat filter), join-path reasoning (picking the correct tables and result grain in a normalized clinical schema), and temporal reasoning (anchoring phrases like “currently on insulin” to real date columns and status logic). Getting any of these wrong doesn’t just crash the query, it silently produces the wrong patient cohort, which is worse.
Existing Text-to-SQL research doesn’t fully cover this setting. Most benchmarks score isolated single-turn questions, so dialogue memory and constraint retention across turns are rarely measured. Most systems generate SQL with one monolithic LLM call, making the reasoning behind a join or filter choice implicit and uninspectable. Schema grounding is usually a static text dump rather than the database’s actual current values, and failure recovery is typically a naive retry rather than a structured response to why a query failed. No existing benchmark stratifies clinical queries by which of these reasoning dimensions (or combinations) they stress.
This project explores an alternative to the single, all-at-once response most systems rely on, using a staged, feedback-driven process rather than one monolithic model call. This is still active, evolving work; further details will be shared once the approach is validated and written up.
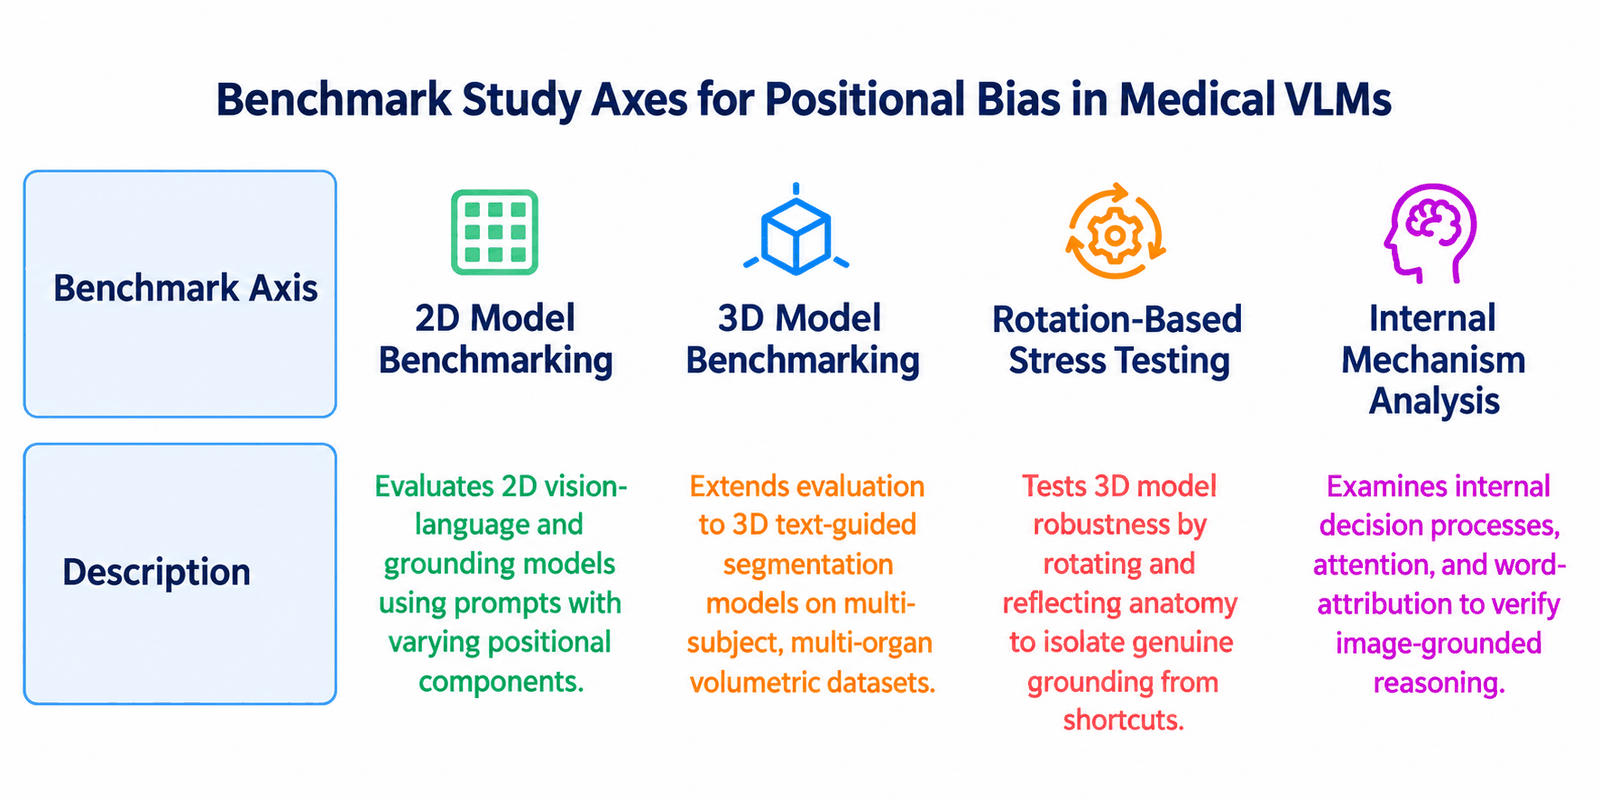
Positional Bias in Medical Vision-Language Models: A Benchmark Study
September 2026 to Present
Medical vision-language models (VLMs) increasingly use natural-language prompts to localize or segment anatomical structures, where positional terms such as left, right, upper, and lower are combined with entity descriptions such as kidney or lobe. However, standard metrics such as Dice and IoU do not reveal whether a model genuinely follows positional instructions or relies on fixed spatial priors, memorized patterns, or other shortcuts. A model may therefore achieve good overall accuracy while failing to correctly respond to positional language.
There is currently no systematic, model-agnostic benchmark for evaluating positional grounding in medical VLMs. Existing evaluations mainly focus on overall localization or segmentation performance, with limited attention to controlled positional prompts, 3D spatial reasoning, geometric stress testing, and the underlying reasons for positional behavior.
We benchmark 2D and 3D medical vision-language models using controlled positional prompts, followed by rotation-based stress tests and internal analysis of positional and entity information. This allows us to evaluate whether models consistently ground positional language in the medical image rather than relying on shortcuts.